Stem cell injections for the shoulder are offered for rotator cuff tears and arthritis, but the research does not yet show that they reliably relieve pain, restore function or regrow tissue, and no stem cell product is FDA-approved for shoulder pain. That is the honest starting point. Early studies are interesting, some patients report feeling better, and serious harm has been uncommon in the published literature. Still, the evidence is thinner than many clinic websites suggest. If you are weighing this option, you deserve to see what is known, what is not, and what to ask before anyone puts a needle in your joint.
TL;DR
- Stem cell injections for the shoulder use cells, usually from your bone marrow or fat, or processed donor tissue. The FDA states that regenerative products have not been approved for orthopedic conditions such as osteoarthritis, tendonitis or shoulder pain.
- For shoulder arthritis, the American Academy of Orthopaedic Surgeons (AAOS) cannot recommend injectable biologics, including stem cells and PRP, because reliable evidence is lacking.
- For rotator cuff tears, trials show mixed results. Cells may lower retear rates after surgery, but they have not clearly improved pain or function.
- PRP (platelet-rich plasma) is a different, more widely studied biologic. It is also not proven for shoulder arthritis, so expectations should be modest.
- A good first step is an exam and imaging to find out what is actually causing your pain, followed by a stepwise plan that starts with the lowest-risk options.
Table of Contents
- What shoulder stem cell therapy actually is
- What the research says for rotator cuff tears
- Stem cells for shoulder arthritis and cartilage
- PRP for shoulder arthritis: how it differs
- What the FDA and CDC say about safety and approval
- How the injection is done and what can go wrong
- How long recovery takes and when to expect change
- Established options to weigh first
- Our perspective
- When a regenerative consultation makes sense
- Frequently asked questions
- Sources
What shoulder stem cell therapy actually is
The phrase covers several different products, and that is part of the confusion. In orthopedics, mesenchymal stem cells (MSCs) can be collected from several tissues, and bone marrow and fat are the most common adult sources. In a typical procedure, a physician draws marrow or fat from your own body (an autologous approach), concentrates it, and injects it into or around the damaged tissue, often under ultrasound guidance.
The second category is donor-derived products, such as processed amniotic or umbilical tissue, which are sold as “stem cell” injections. Many of these contain few or no living cells. The FDA does not treat them as harmless over-the-counter supplies, and the agency’s consumer guidance explains that products meeting the definition of a biologic generally need approval or must be studied under an investigational application.
The idea behind all of them is that the cells, or the signaling molecules they release, may calm inflammation and support repair in tissue that heals slowly. Tendons and cartilage have limited blood supply, which is why they are such attractive targets. The biology is plausible. What is unsettled is whether it translates into outcomes you can feel.
What the research says for rotator cuff tears
This is the area with the most studies, and the picture is consistent: some promise, no clear victory.
- A 2019 meta-analysis of 22 studies found improvements in some measures, including tendon strain, pain and shoulder function, but concluded that larger studies were needed.
- A 2021 systematic review identified 20 eligible shoulder orthobiologic studies, 13 on PRP and 2 on MSCs. Efficacy results were mixed, no serious adverse events were reported, and the authors called the evidence inconclusive for or against treatment, urging standardized product reporting and outcome measures.
- A 2024 review noted that human MSC studies of rotator cuff injuries are limited and heterogeneous, with different formulations, doses and schedules. Randomized trials have mixed results and do not establish lasting structural regeneration.
- A 2025 systematic review of five studies with 228 people looked at adding MSCs during rotator cuff repair. Clinical and functional outcomes were no better than repair alone. Retear risk was lower, though: a relative risk of 0.52 at mid-term follow-up and 0.24 at long-term follow-up. The authors read that cautiously. Tendons may be better protected structurally, but that has not translated into better pain, strength or range of motion.
In plain terms: a tendon that looks better on a scan is not the same as a shoulder that feels better. When we counsel patients, we try to keep those two things separate.
A US health-technology assessment reached a similar conclusion for partial rotator cuff tears, finding the evidence insufficient because it came mainly from case series and poor-quality comparison groups.
Stem cells for shoulder arthritis and cartilage
People searching this topic often hope the answer is “yes, you can regrow cartilage.” Today the evidence does not support that. The AAOS guideline on glenohumeral (ball-and-socket) osteoarthritis states that injectable biologics, including stem cells and PRP, cannot be recommended for shoulder osteoarthritis because reliable evidence is lacking. The same guideline says physical therapy may benefit selected patients, though it labels that a consensus opinion because the underlying evidence is also limited.
The 2021 systematic review above found that none of its included studies addressed glenohumeral osteoarthritis at all. A Mayo Clinic Q&A made the same point years earlier, noting that no major studies had specifically examined stem cell treatment for shoulder arthritis, with most knowledge borrowed from the knee.
That borrowing matters. Knee research is far more abundant, and the shoulder is built differently: a shallow socket, a very mobile joint, and wear patterns that often involve the rotator cuff and the acromioclavicular (AC) joint, not just cartilage. A result in a knee trial cannot simply be assumed for your shoulder.
PRP for shoulder arthritis: how it differs
PRP is made by spinning a small sample of your own blood to concentrate platelets, which carry growth factors, then injecting that plasma into the target area. No cell harvesting from marrow or fat is needed, and the preparation is simpler. It is a separate treatment from stem cells, though people often group them together.
The evidence is more developed, but not decisive:
- A 2021 meta-analysis found no serious adverse events in nine trials, though three trials reported injection intolerance, frozen shoulder or tear worsening.
- The 2025 AAOS rotator cuff guideline strongly recommends against platelet-derived products to improve patient-reported outcomes after repair, although limited evidence suggests liquid PRP may reduce some retear rates.
- AAOS commentary from 2026 says PRP may improve rotator cuff structure, but clinical outcomes are inconclusive and variation in preparation limits interpretation.
- A Federal Employee Program policy review classifies PRP as investigational for orthopedic uses, including osteoarthritis and rotator cuff repair. That has a practical consequence: many insurers will not cover it, and you should ask about cost before treatment.
Preparation variability deserves emphasis. “PRP” can mean very different platelet concentrations, with or without white blood cells, from device to device. Two patients told they received PRP may have received quite different products. For a closer look at our approach to the shoulder, see how effective PRP injections are for shoulder pain.
What the FDA and CDC say about safety and approval
The regulatory position is clear and worth reading for yourself. The FDA says regenerative medicine products have not been approved to treat orthopedic conditions including osteoarthritis, tendonitis or shoulder pain, and that before approval they require FDA oversight in a clinical trial. The agency lists possible harms from illegally marketed products: infection, contamination, unwanted immune or inflammatory responses, migration or inappropriate tissue growth, tumor formation, neurological events and treatment failure.
The CDC has issued a similar warning, stating that unapproved stem cell and exosome products expose patients to risks without a clear proven benefit, including injection-site reactions, infection and contamination.
The practical lessons are these:
- Ask exactly what is being injected, where it comes from, and whether it is your own tissue.
- Ask whether the treatment is part of a registered clinical trial, and whether you will be asked to sign an informed consent describing it as investigational.
- Be wary of any provider who promises cartilage regrowth, avoiding surgery, or a success percentage without citing a published study.
- Be wary of “free seminars” that pair a pitch with high-pressure same-week scheduling.
We discuss the same regulatory picture for other joints in our posts on stem cell therapy and the lack of FDA approval for arthritis and back stem cell products.
How the injection is done and what can go wrong
The procedure is usually short. For a bone marrow product, the clinician numbs the skin over the hip bone, draws marrow, processes it in a centrifuge, and then injects the concentrate into the shoulder with ultrasound or fluoroscopic guidance. PRP skips the marrow step and starts with a blood draw. Either way, the injection itself typically takes under an hour in the room, though appointment length varies by practice.
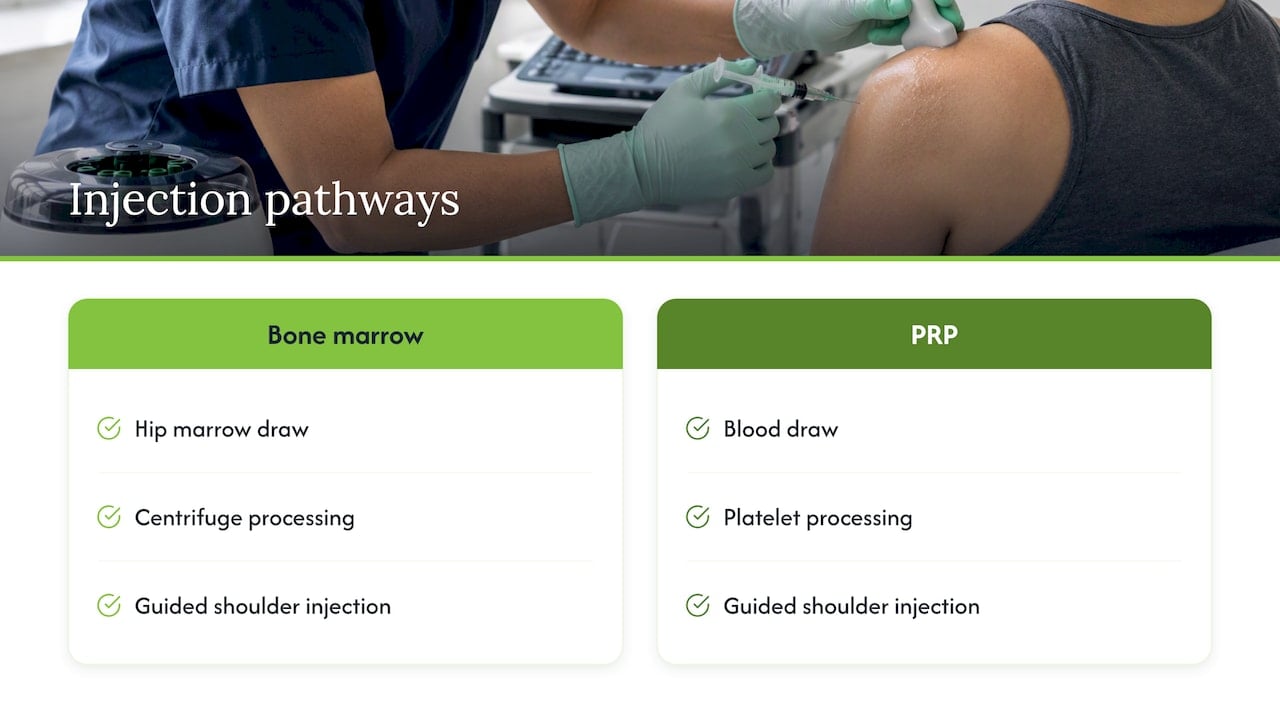
The common downside is post-injection soreness, which can last days. Less common complications described in a review of ultrasound-guided PRP procedures include septic arthritis, cellulitis, osteomyelitis, allergic reaction, skin discoloration, blood clots, adhesive capsulitis (frozen shoulder) and tendon rupture after injection into the tendon. These are rare, but they are the reason sterile technique and imaging guidance matter. Cost is the other downside: when treatment is investigational, it is often paid out of pocket.
How long recovery takes and when to expect change
Published studies use different products and follow-up periods, so no single timeline applies to everyone. What we tell patients, based on how biologic treatments behave generally, is this:
- First few days: Soreness, stiffness and sometimes a temporary flare in pain are common. Avoid heavy lifting and overhead work as instructed.
- First weeks: Many people return to light daily activity quickly, but a structured rehabilitation program usually begins in this window.
- One to three months: If a response occurs, it tends to be gradual, not immediate. A reasonable first reassessment point is around this time.
- Three to six months or longer: Tendon and joint tissue remodel slowly, so strength and function changes, if any, appear late.
We would not promise any of this. Some patients improve noticeably, some partially, and some not at all. Many patients come to us after cortisone shots, anti-inflammatories and months of home exercises, and they are understandably looking for something that does more than quiet the pain for a few weeks. We try to be direct that a biologic injection is one tool, and that the rehabilitation you do afterward often shapes the result as much as the injection does.
Established options to weigh first
Because the evidence for stem cells is limited, it helps to know what has a stronger track record.
| Option | What it is used for | What the evidence supports |
|---|---|---|
| Physical therapy | Rotator cuff problems, early to moderate arthritis, stiffness | Recommended for selected arthritis patients by AAOS as a consensus opinion; widely used first-line for cuff tears |
| Activity modification and anti-inflammatory medication | Flare-ups | Short-term symptom control |
| Corticosteroid injection | Pain flares from inflammation | Short-term relief; repeated use can be a concern for tendon health |
| PRP | Tendon problems, selected joint pain | Mixed, investigational; low serious-risk profile in trials |
| Stem cell products | Cuff tears, arthritis | Preliminary; not FDA-approved for the shoulder |
| Surgery (cuff repair, shoulder replacement) | Full-thickness tears, advanced arthritis | The established option when conservative care fails |
For patients with a partial tear or tendon degeneration, we often start with a supervised therapy program. Our physical therapy team builds exercise around scapular control and cuff strength. Some patients also ask about light-based treatments for joint stiffness; if you are curious, there is general reading on red light therapy for arthritis, though it should be viewed as a comfort-oriented adjunct, not a substitute for a diagnosis.
If you want to understand how much function is realistic without an operation, our article on recovering from a rotator cuff tear without surgery walks through the numbers.
Our perspective
We think the most useful thing a clinic can do is slow the conversation down. The word “stem cell” carries a lot of hope, and patients who are tired of pain are the most likely to hear a promise that was never made. Our view is shaped by what we see in practice and by the guidelines above.
First, diagnosis comes before any injection. A shoulder that hurts at night, aches down the arm and limits reaching may be a cuff tear, arthritis, a pinched neck nerve or a combination. Treating the wrong source will fail with any product.
Second, we separate what is proven from what is plausible. Where guidelines do not support a treatment, we say so, and we explain that PRP and other biologics are investigational for shoulder arthritis. A patient who understands that going in can make a clear decision, including a decision to wait or to try therapy first.
Third, biologics are not a shortcut around rehabilitation. Our regenerative approach pairs any injection with a graded exercise plan, because a tendon that heals still has to be loaded correctly.
Finally, surgery remains the right answer for some shoulders. Avoiding it is a reasonable goal, not a promise. When a full-thickness tear or advanced joint damage is clearly the problem, we will tell you.
— Felix
When a regenerative consultation makes sense
If you have had shoulder pain for months despite therapy and medication, a consultation can clarify whether a biologic option is reasonable for your specific condition. At Nortex Spine and Joint we offer PRP therapy for shoulder pain, along with broader regenerative medicine and rehabilitation services at our North Dallas area locations. You can read about our stem cell program as well. Our physicians are board-certified and Harvard fellowship-trained, and we will review your imaging, discuss realistic outcomes and cover costs before recommending anything. You can start from the Nortex Spine and Joint home page to request an appointment.
Frequently asked questions
What are the downsides of stem cell injections for the shoulder?
The main downsides are uncertain benefit, out-of-pocket cost and procedural risks such as soreness, infection or, rarely, tendon injury. The FDA also warns about contaminated or improperly processed products from unregulated sources. Asking where the product comes from and whether it is your own tissue reduces some of that risk.
Can I regrow cartilage in my shoulder?
Not with any treatment proven today. The AAOS glenohumeral osteoarthritis guideline does not recommend stem cell or PRP injections because reliable evidence is lacking. Therapy, activity changes and, when needed, surgery remain the established paths.
Do stem cells help a torn rotator cuff?
Possibly in limited ways. Reviews show mixed results, and the 2025 analysis found lower retear rates after repair with added cells but no better pain or function than repair alone. They are best regarded as experimental.
Is PRP better than stem cells for shoulder arthritis?
Neither is proven for shoulder arthritis. PRP has more studies behind it and a simpler preparation, but guidelines still describe the evidence as insufficient or inconclusive. The choice depends on your diagnosis, your goals and what you are willing to pay for an investigational option.
Sources
- FDA: Important Patient and Consumer Information About Regenerative Medicine Therapies
- AAOS: Management of Glenohumeral Joint Osteoarthritis
- AAOS: Management of Rotator Cuff Injuries (2025)
- AAOS Now: Orthobiologics expands treatment for rotator cuff tears
- Cell-Based Therapies for Rotator Cuff Injuries: An Updated Review
- Stem Cells in Rotator Cuff Injuries and Reconstructions: A Meta-analysis
- Non-operative orthobiologic use for rotator cuff disorders
- The role of injections of mesenchymal stem cells as an augmentation in rotator cuff repair
- Can platelet-rich plasma injections provide better pain relief in shoulder disorders?
- Health technology assessment: Musculoskeletal Conditions stem cell report
- FEP Medical Policy: Orthopedic Applications of PRP
- CDC: Stem Cell and Exosome Products
- Anaesthetics, steroids and platelet-rich plasma (PRP) in ultrasound-guided musculoskeletal procedures
- Red Light Therapy for Arthritis and Bone Health