Conventional thermal radiofrequency ablation is commonly covered by U.S. health plans, including Medicare, when you meet two conditions: you have completed a documented course of conservative care, and your diagnostic nerve block showed meaningful pain relief. Newer variations, cooled, pulsed, endoscopic, or cryoablation, are frequently denied as investigational. The diagnostic block is usually the starting point for evaluation.
TL;DR:
- Most payers require documented conservative care trials and diagnostic blocks showing significant, lasting pain relief before approving RFA.
- Medicare and commercial plans generally favor medial branch blocks over intra-articular injections for accurate diagnostic prediction.
- Repeated RFA procedures need evidence of sustained pain relief, with limits typically set at two treatments per year per region.
- Newer RFA variants like cooled or pulsed are often classified as investigational, making conventional thermal RFA the most reliably covered option.
- Preparing detailed documentation and understanding specific insurer policies enhance chances of first-time preauthorization approval.
Table of Contents
- What most U.S. payer policies require to approve RFA
- How diagnostic blocks gatekeep coverage and what to document
- Payer positions and CPT codes to bring to your insurer
- Step-by-step checklist to maximize preauthorization success
- What patients consistently misunderstand about RFA coverage
- How Nortex Spine and Joint helps North Dallas patients navigate coverage
- Authoritative policies and guidelines to consult
- A practical next step if you’re weighing RFA in North Dallas
- Sources
- FAQ
What most U.S. payer policies require to approve RFA
Patients often come to us assuming that a positive diagnosis and a referral are enough to get RFA approved. In practice, insurers look for a specific pattern of documentation before they consider the procedure medically necessary, and missing even one piece can mean a denial that delays care by weeks.
Medicare’s Local Coverage Determination for facet joint interventions lays out this pattern clearly. Thermal RFA carries evidence supporting its use for lumbar and cervical facet-mediated pain, and the LCD for facet joint interventions requires diagnostic medial branch blocks before approving denervation, along with limits on how often the procedure can be repeated. Commercial payers largely mirror this structure, though the specific thresholds vary by plan.
Across most policies, you will need to show:
- A documented trial of conservative care, generally including physical therapy, medication management, and activity modification over a suitable period rather than a single visit.
- One or more diagnostic blocks showing pain relief that meets your payer’s criteria and lasts in line with the anesthetic’s expected action.
- Some evidence of improved function following the block, beyond simple pain scores, as insurers value improved mobility or activity tolerance.
- Absence of disqualifying factors, such as prior spinal fusion at the treated level, untreated radiculopathy, or a diagnostic workup that never ruled out other causes of pain.
Repeat procedures typically require documentation of meaningful pain relief lasting several months before insurers approve another RFA in the same area, reflecting the temporary nature of the treatment.
How diagnostic blocks gatekeep coverage and what to document
Medial branch blocks are generally preferred over intra-articular facet injections as diagnostic tools because they focus on the nerve likely responsible for pain, providing a clearer prediction of RFA’s potential benefit. An intra-articular injection can numb the joint itself, but it does not tell you whether ablating the nerve will replicate that relief, which is why most payer policies specifically ask for MBB or genicular nerve block results rather than any injection near the joint.
Payers often require documentation of:
- The percent of pain relief measured on standard scales shortly after the block and again at a defined follow-up.
- A duration of relief consistent with the expected effect of the anesthetic used, since unusually short or prolonged relief can raise concerns.
- Functional improvement details, such as better walking tolerance or reduced medication needs, together with pain score changes.
- Imaging confirmation during the procedure (usually fluoroscopy) verifying accurate needle placement to support the block’s validity.
Pro Tip: If your relief after a single block falls just below your payer’s threshold, ask your physician about a second confirmatory block before submitting for RFA. A borderline first result rarely improves on appeal without new evidence, but a well-documented second block often does.
A lumbar medial branch block is usually the first diagnostic step for low-back facet pain, and a cervical medial branch block serves the same purpose for neck pain. When results are ambiguous, some patients continue conservative therapy a bit longer, others repeat the block, and a smaller group needs a physician letter prepared specifically for a peer-to-peer call with the insurer’s medical director.
Payer positions and CPT codes to bring to your insurer
Knowing how a specific insurer classifies each RFA variant saves you from surprises at the preauthorization stage. UnitedHealthcare’s ablative treatment policy lists pulsed RFA, cooled RFA, endoscopic RFA, and cryoablation as unproven for most facet denervation indications, while conventional thermal RFA remains the modality most consistently approved. Aetna’s medical policy bulletin is similarly specific: it considers standard, non-pulsed radiofrequency facet denervation medically necessary when a patient has chronic disabling pain, has failed conservative care, has no prior fusion at the level, and has two positive diagnostic blocks with strong relief, but it does not cover cooled RFA for this indication. BCBSNC’s coverage update on genicular nerve blocks and peripheral nerve ablation follows the same logic for knee pain, treating advanced variants as investigational absent stronger comparative evidence.
Common CPT codes cover facet joint denervation and diagnostic injections; unlisted codes, used for newer devices, can trigger manual review rather than automatic approval.
Payers consistently favor thermal RFA over newer variants because its evidence base is larger and more consistent, which is what makes conventional RFA the modality most likely to clear utilization review even as competing devices reach the market (interventional pain management guideline review).
Frequency limits matter too:
- Many policies limit RFA treatments to no more than twice per treated region within a year.
- UnitedHealthcare’s facet joint injections policy recommends repeat RFA only when the prior procedure produced at least half relief lasting several months, with a minimum interval of about six months between repeat procedures at the same level.
- An unlisted code paired with thin documentation is one of the most common reasons a straightforward case gets stuck in review.
Step-by-step checklist to maximize preauthorization success
Getting RFA approved on the first submission usually comes down to preparation, not persistence. Here is the sequence we walk patients through.
- Gather your conservative-care timeline. List every physical therapy course, medication trial, and activity modification attempt, with dates and outcomes, including options like laser therapy for neuropathy to understand evidence-led noninvasive pain therapies.
- Compile your imaging summary. Include reports that rule out surgical pathology, since payers want confirmation that RFA, not surgery, is the appropriate next step.
- Document your diagnostic block results in detail. Record baseline pain, post-block pain, percent relief, and any functional change, ideally in the same note your physician sends to the insurer.
- Request the insurer’s specific medical policy or LCD number. Ask your plan directly which policy governs your case and cite that reference number in your authorization packet rather than assuming a generic standard applies.
- Prepare for a possible peer-to-peer review. If the initial request is denied, your clinic should be ready to have the treating physician speak directly with the payer’s medical director, referencing the specific guideline language and your functional metrics.
- Ask about external review if the appeal fails. Every state has a process for independent external review once internal appeals are exhausted, and your insurer is required to explain how to request one.
- Discuss scheduling contingencies. Ask your clinic whether you can hold a tentative date while authorization is pending, and get a candid out-of-pocket estimate in case the payer ultimately denies the specific modality proposed.
Pro Tip: Keep a single document with your conservative-care dates, block results, and policy reference number. When a peer-to-peer call happens on short notice, having everything in one place is often the difference between a same-day approval and another two-week delay.
What patients consistently misunderstand about RFA coverage
The biggest misconception we see is that insurance denial means the treatment does not work. Denials usually reflect a documentation gap or a payer’s specific classification of the device used, not a judgment on RFA’s clinical value. Conventional thermal RFA has a real, if temporary, effect for many patients with facet-mediated pain, but it is not a permanent fix, since the ablated nerve typically regenerates over months, which is exactly why insurers write repeat-procedure rules instead of leaving the door open indefinitely.
The second misunderstanding is assuming newer technology automatically means better coverage. Cooled and pulsed RFA are marketed as improvements, but most major payers still classify them as investigational because the comparative evidence has not caught up to the marketing. Patients who insist on a specific device without checking their plan’s stance often end up paying out of pocket for something a covered alternative would have addressed just as well.
— Felix
How Nortex Spine and Joint helps North Dallas patients navigate coverage
Our clinic screens every RFA candidate with diagnostic blocks first and documents conservative care thoroughly before submitting a request for the procedure itself. That sequence exists because it mirrors what payers actually require, not just what makes clinical sense to us.
Our team prepares authorization packets that include the conservative-care timeline, block results with percent relief, and a physician rationale connecting your specific anatomy to your symptoms, and we support peer-to-peer discussions when a payer’s first response is a denial. We offer an insurance benefits check before you commit to a treatment plan, and if a payer classifies your specific modality as investigational, a candid out-of-pocket estimate is provided so you can decide with full information.
If you already know your insurer’s policy name or your Medicare LCD number, bring it to your consultation. It lets us assess your coverage picture quickly instead of starting from zero.
Authoritative policies and guidelines to consult
Keep these on hand when you talk with your insurer or prepare an appeal: the Medicare LCD for facet joint interventions for Medicare-specific criteria, Aetna’s back pain invasive procedures bulletin for detailed commercial eligibility rules, and UnitedHealthcare’s ablative treatment and facet joint injections policies for CPT and frequency guidance. BCBSNC’s genicular nerve block update covers knee-specific coverage patterns. Save these links before your consultation or appeal.
A practical next step if you’re weighing RFA in North Dallas
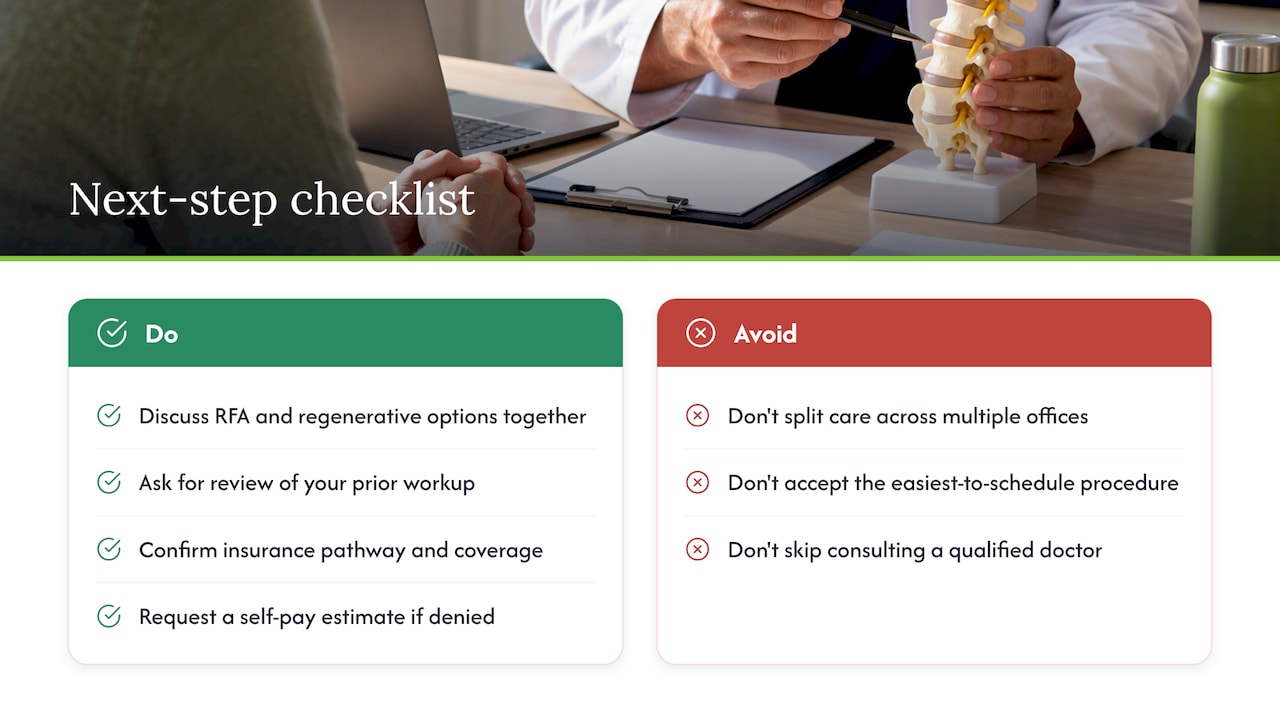
If you have already tried physical therapy and medication without lasting relief, RFA may be worth exploring, but so may regenerative options depending on your diagnosis and what your plan will cover. Nortex Spine and Joint offers regenerative medicine alongside back pain therapy that includes RFA, so you can discuss both the insurance pathway and the clinical fit for your case in one visit rather than piecing it together across multiple offices.
Some clinics have fellowship-trained and board-certified physicians, and treatment plans typically start with a review of your prior workup, not a default to whichever procedure is easiest to schedule. If a payer denies your specific RFA modality, a self-pay estimate can be provided along with discussion of whether a covered alternative makes more clinical sense. Schedule a consultation through our back pain therapy page to get a straight answer on where you stand.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- BCBSNC policy update, genicular nerve blocks and peripheral nerve ablation
- LCD – Facet Joint Interventions for Pain Management (L38841)
- UnitedHealthcare – Ablative treatment for spinal pain (commercial policy)
- Aetna – Back Pain – Invasive Procedures (medical policy bulletin)
FAQ
Is radiofrequency ablation usually covered by insurance?
Conventional thermal RFA is commonly covered when you meet conservative-care and diagnostic-block requirements, while cooled, pulsed, endoscopic, and cryoablation variants are frequently denied as investigational under policies like UnitedHealthcare’s. Coverage depends heavily on documentation, particularly your diagnostic block results.
How many diagnostic blocks does insurance require before RFA?
Many commercial payers, including Aetna, require two positive diagnostic blocks with strong pain relief before approving RFA, though some policies accept one block with clear documentation. Medicare’s requirements vary by local contractor under the applicable LCD.
What percent pain relief do I need from a diagnostic block?
Payers generally look for substantial relief, often described as significant improvement on a standard pain scale, that lasts as long as the anesthetic’s expected duration. The exact threshold is set by your specific plan’s medical policy, so confirming the number with your insurer avoids surprises.
How often can I repeat RFA if it wears off?
Most policies allow no more than two RFA procedures per treated region within a rolling twelve-month period, and repeat approval typically requires documented relief of at least half your pain lasting several months after the prior procedure. Nerves regenerate over time, which is why RFA is considered a repeatable rather than permanent treatment.
What if my insurer denies RFA as investigational?
You can request a peer-to-peer review where your physician discusses your case directly with the payer’s medical director, followed by a formal appeal if that fails. Every state also offers an external review process once internal appeals are exhausted.